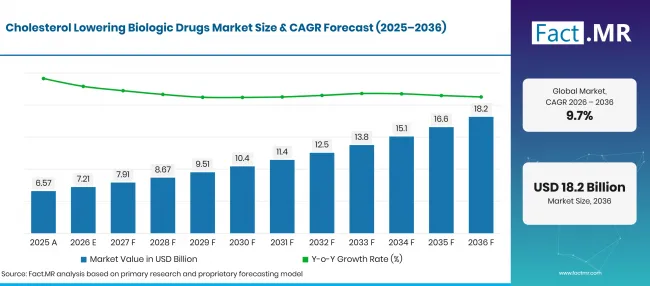
- Market Value (2025): USD 6.57 Bn
- Estimated Value (2026): USD 7.2 Bn
- Forecast Value (2036): USD 18.2 Bn
- CAGR (2026-2036): 9.7%
What is the Cholesterol Lowering Biologic Drugs Market forecast to be worth by 2036?
USD 7.2 billion in 2026 to USD 18.2 billion by 2036 at a 9.7% CAGR.
- As per Fact.MR analysis, the cholesterol lowering biologic drugs market reached USD 6.57 billion in 2025.
- Demand will increase from USD 7.2 billion in 2026 to USD 18.2 billion by 2036.
- The cholesterol lowering biologic drugs market will record 9.7% CAGR from 2026 to 2036.
Cholesterol Lowering Biologic Drugs Market Taxonomy (11) | Source: Fact.MR
What are the defining numbers behind Cholesterol Lowering Biologic Drugs Market growth?
An absolute opportunity of USD 11.0 billion will be created between 2026 and 2036.
- Demand Drivers in the Market
- Cardiovascular disease keeps a large pool of patients in need of LDL cholesterol control. The World Health Organization reported that an estimated 19.8 million people died from cardiovascular diseases in 2022, about 32% of all global deaths [1].
- Raised cholesterol is common and often undertreated. The World Health Organization estimated in September 2026 that 39% of adults worldwide have raised total cholesterol [2]. High-risk patients who stay above target on statins will become candidates for add-on therapy.
- Outcome evidence gives prescribers confidence. The FOURIER trial of evolocumab and the ODYSSEY Outcomes trial of alirocumab showed fewer major cardiovascular events in high-risk patients on statins.
- Less frequent dosing will support persistence on therapy. Novartis said in July 2025 that the U.S. FDA approved twice-yearly Leqvio for use without a statin [3]. Fewer administrations suit patients who struggle with regular injections.
- Key Segments Analyzed
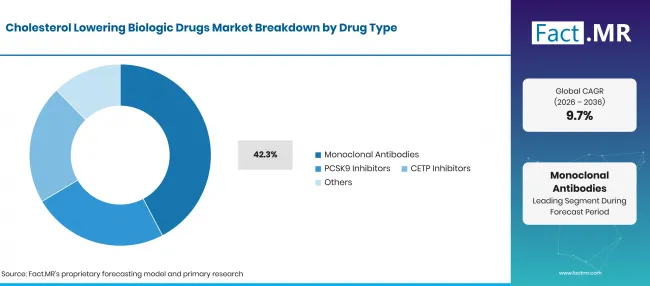
- By Drug Type: Monoclonal Antibodies will hold 42.3% share in 2026 since evolocumab and alirocumab carry the longest clinical record and outcome trial support.
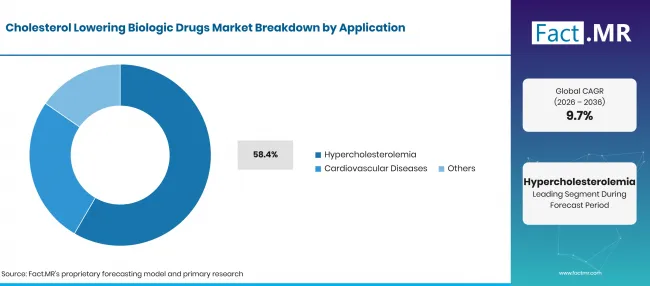
- By Application: Hypercholesterolemia will account for 58.4% share in 2026, supported by labels that target elevated LDL cholesterol in familial and statin-intolerant patients.
- By Distribution Channel: Retail Pharmacies will capture 59.7% share in 2026 owing to outpatient care and self-injection with prefilled pens on a chronic schedule.
- Analyst Opinion at Fact.MR
- Shambhu Nath Jha, Principal Consultant at Fact.MR, states, “Cholesterol lowering biologics will become a standard step for high-risk patients who miss LDL goals on statins. Antibodies will keep the lead on the strength of outcome data. Oral PCSK9 and CETP drugs will compete on convenience and price until their own outcome trials report.”
- Strategic Implications
- Manufacturers should publish real-world goal attainment and persistence data, since payers want proof that therapy stays in use.
- Antibody makers should prepare for oral PCSK9 and CETP competition by building value cases on outcome data, long-term safety and total cost of care.
- Payers and health systems should set clear step criteria for add-on therapy, given that delays between a cardiac event and treatment leave patients above target for months.
The United States will lead at 11.9% CAGR, supported by a broad label for PCSK9 therapy and direct-to-patient supply. The United Kingdom will follow at 11.0% as NHS programs widen cholesterol testing. Sweden will record 10.5% with registry-guided care after heart attack. Belgium will post 9.1% under defined access criteria for high-risk groups. Germany will reach 8.3% within strict prescribing conditions. Japan will grow at 7.7% with specialist-led lipid care, while Italy will close at 6.9% under national prescribing controls.
How does the Cholesterol Lowering Biologic Drugs Market break down by segment?
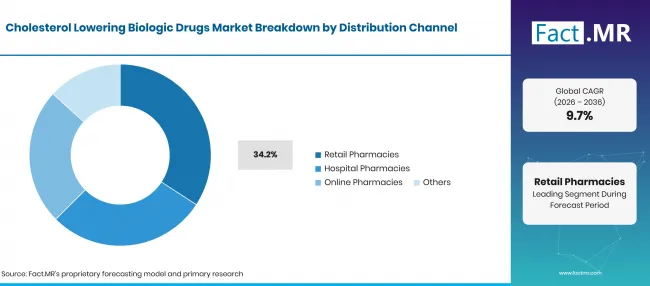
Monoclonal Antibodies will lead Drug Type at 42.3%; Hypercholesterolemia will lead Application at 58.4%; Retail Pharmacies will lead Distribution Channel at 34.2%.
Which Drug Type dominates?
Monoclonal Antibodies will hold 42.3% share in 2026.
Cholesterol Lowering Biologic Drugs Market Taxonomy (4) | Source: Fact.MR
Monoclonal antibodies will lead because evolocumab and alirocumab were the first PCSK9-targeting products and carry outcome trial evidence. Evinacumab extends the class into homozygous familial disease by blocking ANGPTL3. Supply depends on biologics manufacturing capacity in mammalian cell culture.
The PCSK9 Inhibitors subsegment covers non-antibody agents such as the siRNA inclisiran and oral peptides. Merck said in July 2026 that the U.S. FDA approved Lipfendra, a once-daily macrocyclic peptide, as the first oral PCSK9 inhibitor [4]. CETP inhibitors are oral small molecules, and the European Medicines Agency’s CHMP adopted a positive opinion for obicetrapib (Ubeslo) on 23 July 2026 [5].
What leads the Application segment?
Hypercholesterolemia will account for 58.4% share in 2026.
Cholesterol Lowering Biologic Drugs Market Taxonomy (2) | Source: Fact.MR
Hypercholesterolemia will lead since elevated LDL cholesterol is the direct target on most labels, including familial disease and statin-intolerant patients. The World Health Organization estimated that familial hypercholesterolaemia affects 1 in 250 to 1 in 300 people globally [2].
Cardiovascular diseases cover use to cut heart attack and stroke risk in adults with established disease. This group overlaps with atherosclerosis drugs and will gain weight as outcome data support earlier use after an acute coronary event.
How does Distribution Channel shape demand?
Retail Pharmacies will capture 34.2% share in 2026.
Cholesterol Lowering Biologic Drugs Market Taxonomy (3) | Source: Fact.MR
Retail pharmacies will lead owing to outpatient treatment and home self-injection on a chronic schedule. Community pharmacists manage refills and cold storage, and they counsel patients on autoinjector devices at the first fill.
Hospital pharmacies handle initiation after acute coronary syndrome and infused evinacumab. Online pharmacies are gaining use through direct-to-patient models. Amgen stated that all U.S. patients can now obtain Repatha through AmgenNow, its direct-to-patient program [6]. Prior authorization and cold-chain needs will limit how fast online channels grow.
What is accelerating Cholesterol Lowering Biologic Drugs Market adoption, and what is holding it back?
Demand will rise through a large high-risk cardiovascular population and guidance that supports add-on therapy for patients who miss LDL goals. Growth is constrained by treatment cost, payer restrictions and competition from oral and long-acting options.
Drivers Impact Analysis
| DRIVER | (~) % IMPACT ON CAGR | GEOGRAPHIC RELEVANCE | IMPACT TIMELINE |
|---|---|---|---|
| Cardiovascular disease burden and LDL goal shortfall on statins | +2.1% | Global | Short term (<= 2 years) |
| Guidance favoring lower LDL targets and earlier add-on therapy | +1.7% | North America, Western Europe | Medium term (2-4 years) |
| Cardiovascular outcome evidence for PCSK9-targeting antibodies | +1.2% | Global | Medium term (2-4 years) |
| Less frequent dosing that improves persistence | +0.8% | Global | Long term (>= 4 years) |
Opportunity Impact Analysis
| OPPORTUNITY | (~) % IMPACT ON CAGR | GEOGRAPHIC RELEVANCE | IMPACT TIMELINE |
|---|---|---|---|
| Earlier use in high-risk primary prevention | +1.3% | North America, Western Europe | Long term (>= 4 years) |
| Direct-to-patient and online dispensing models | +0.9% | North America | Medium term (2-4 years) |
| Oral PCSK9 and CETP launches for needle-averse patients | +0.7% | North America, Western Europe | Medium term (2-4 years) |
Restraints Impact Analysis
| RESTRAINT | (~) % IMPACT ON CAGR | GEOGRAPHIC RELEVANCE | IMPACT TIMELINE |
|---|---|---|---|
| High treatment cost and prior authorization requirements | -1.0% | Global | Short term (<= 2 years) |
| Price pressure from oral entrants and generic statins | -0.7% | North America, Western Europe | Medium term (2-4 years) |
| Under-diagnosis and treatment discontinuation | -0.4% | Global | Long term (>= 4 years) |
Which countries are scaling the Cholesterol Lowering Biologic Drugs Market through 2036?
- The country comparison spans 5.0 percentage points between the United States at 11.9% and Italy at 6.9%.
- The United States will keep a 0.9-point lead over the United Kingdom, helped by a broader label for PCSK9 therapy and the first oral PCSK9 approval.
- Pharmacy-based cholesterol checks will give the United Kingdom a 0.5-point edge over Sweden as more high-risk adults are found in primary care.
- A 1.4 percentage point gap separates Sweden from Belgium, since registry follow-up after heart attack keeps Swedish patients on intensified lipid care.
- In Belgium, defined access criteria for high-risk groups will leave the country 0.8 points clear of Germany.
- Strict G-BA prescribing conditions cap volumes yet keep Germany 0.6 points above Japan.
- Japan will hold a 0.8-point lead over Italy, supported by an aging population and specialist-guided care for familial disease.
- Italy will close the range, where national prescribing rules confine biologic use to defined patient groups.
Comparable CAGRs create different entry conditions, since reimbursement rules, prescriber limits and cardiovascular disease burden vary by country. Full report coverage includes North America, Latin America, Western Europe, Eastern Europe, East Asia, South Asia & Pacific, Middle East & Africa.
As per Fact.MR, global cholesterol lowering biologic drug consumption is estimated at USD 0.87 per capita in 2026, compared with USD 0.80 per capita in 2025. It will grow to USD 2.04 per capita by 2036 as more high-risk patients move from statins alone to add-on PCSK9 or CETP therapy. Demand will rise across cardiology clinics, primary care practices, retail pharmacies and direct-to-patient programs in both mature and emerging health systems. As per Fact.MR, the growth of cholesterol lowering biologics will come less from new patients with rare familial disease and more from earlier use after heart attack, lower-cost oral options and wider payer coverage.
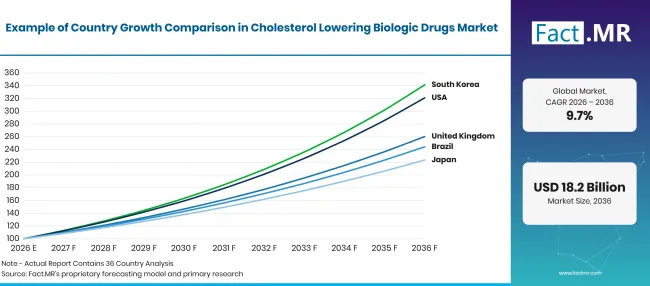
Cholesterol Lowering Biologic Drugs Market Taxonomy (13) | Source: Fact.MR
| Country | CAGR (2026-2036) |
|---|---|
| United States | 12.4% |
| United Kingdom | 11.0% |
| Sweden | 10.5% |
| Belgium | 9.1% |
| Germany | 8.3% |
| Japan | 7.7% |
| Italy | 6.9% |
What supports United States adoption?
12.4% CAGR, supported by broader labels and new oral PCSK9 options.
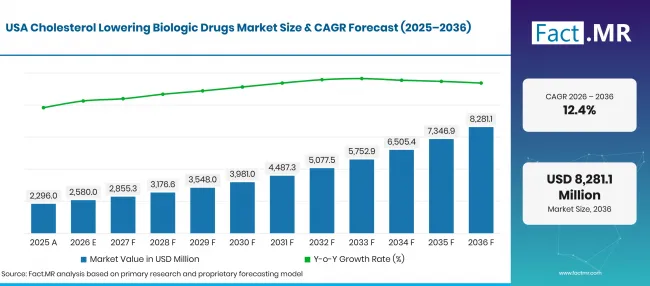
Cholesterol Lowering Biologic Drugs Market Taxonomy (12) | Source: Fact.MR
The National Center for Health Statistics reported 683,491 heart disease deaths in 2024, or 22.2% of all deaths [7]. Amgen said that the FDA broadened Repatha’s approved use in 2025 to adults at increased risk of cardiovascular events due to uncontrolled LDL cholesterol [6].
How is the United Kingdom scaling demand?
11.0% CAGR, aided by NHS programs that widen cholesterol testing.
NHS England said in August 2026 that around 100 community pharmacies will offer cholesterol checks to people aged 40 to 84 [8]. Its north London pilot found one in five people tested at high risk [8]. More detected patients will enter lipid pathways that add biologic therapy for those who stay above target.
What supports Sweden’s growth?
10.5% CAGR, backed by registry-guided secondary prevention.
Swedish cardiology units track LDL cholesterol after myocardial infarction through the SWEDEHEART registry, which flags patients above target. Socialstyrelsen reported that about 20,300 people in Sweden had an acute myocardial infarction in 2024 and about 4,000 died with one [9]. Each new patient will enter structured follow-up.
How is Belgium developing demand?
9.1% CAGR, underpinned by defined access for high-risk patients.
Sciensano reported that age-adjusted cardiovascular mortality fell by 30% in men and 28% in women between 2012 and 2022 [10]. Specialist initiation and documented LDL cholesterol levels shape access to biologic therapy. These conditions keep uptake steady while limiting volumes outside high-risk groups.
What is supporting Germany’s adoption?
8.3% CAGR, anchored by rule-based prescribing for high-risk patients.
The Federal Statistical Office reported 339,212 deaths from circulatory diseases in 2024 [11]. The Federal Joint Committee limits evolocumab, alirocumab and inclisiran to patients whose LDL cholesterol stays uncontrolled after 12 months of documented maximal lipid-lowering therapy [12]. Only named specialists may initiate therapy, which caps volumes but gives prescribers a clear route [12].
How does Japan perform?
7.7% CAGR, led by an aging population and specialist-guided lipid care.
Japan’s health ministry reported 226,388 heart disease deaths in 2024, or 14.1% of all deaths [13]. Prescribing follows Japan Atherosclerosis Society guidance and stays with specialists. Familial disease and high-risk secondary prevention will remain the main uses.
What is shaping Italy’s demand?
6.9% CAGR, held back by national prescribing controls.
ISTAT reported 206,119 deaths from circulatory diseases in 2023, or 31% of all deaths [14]. In March 2025, the medicines agency AIFA changed the list of prescribers for evolocumab, alirocumab and inclisiran through Determina 252/2025 [15]. These controls promote appropriate use but slow growth beyond defined patient groups.
Who leads the Cholesterol Lowering Biologic Drugs Market?
Competition falls into three tiers. Amgen, Regeneron and Sanofi hold the antibody tier, where Repatha and Praluent compete on outcome evidence and payer contracts. Amgen widened that evidence in November 2025, when VESALIUS-CV showed fewer first cardiovascular events in high-risk patients without a prior heart attack or stroke [6]. Novartis leads a second tier built on dosing convenience with twice-yearly Leqvio. Oral and one-time therapies form the third tier. Merck gained U.S. approval for Lipfendra in July 2026 [4]. AstraZeneca has its oral PCSK9 candidate laroprovstat in Phase III, and NewAmsterdam Pharma is taking obicetrapib through European review with Menarini. Eli Lilly reported in May 2026 that one dose of its base editor VERVE-102 gave durable LDL cholesterol lowering in an early trial [16]. Competition will turn on whether oral and one-time options can match antibody outcome data at a lower cost to payers.
Which companies are the key providers?
Key companies include Amgen Inc.; Regeneron Pharmaceuticals Inc.; Sanofi S.A.; Novartis AG; Merck & Co., Inc.; AstraZeneca plc; Eli Lilly and Company (including Verve Therapeutics); and NewAmsterdam Pharma Company N.V.
- Amgen Inc.
- Regeneron Pharmaceuticals Inc.
- Sanofi S.A.
- Novartis AG
- Merck & Co., Inc.
- AstraZeneca plc
- Eli Lilly and Company (including Verve Therapeutics)
- NewAmsterdam Pharma Company N.V.
Bibliography
- [1] World Health Organization. (2025, July 31). Cardiovascular diseases (CVDs).
- [2] World Health Organization. (2026, September 15). Dyslipidaemia.
- [3] Novartis. (2025, July 31). Novartis twice-yearly Leqvio (inclisiran) receives FDA approval for new indication enabling first-line use.
- [4] Merck & Co., Inc. (2026, July 16). Merck’s LIPFENDRA (enlicitide) is the First and Only Once-Daily Oral PCSK9 Inhibitor Approved by the U.S. FDA to Reduce LDL-C in Adults with Hypercholesterolemia.
- [5] European Medicines Agency. (2026, July 24). Ubeslo.
- [6] Amgen. (2025, November 8). Amgen’s Repatha cuts risk of first major adverse cardiovascular events by 25% in landmark Phase 3 VESALIUS-CV trial.
- [7] National Center for Health Statistics. (2026, January). Mortality in the United States, 2024 (NCHS Data Brief No. 548).
- [8] NHS England. (2026, August). High-street pharmacies to launch seven-minute cholesterol checks.
- [9] Socialstyrelsen. (2026, January 12). Statistik om hjärtinfarkter [Statistics on myocardial infarctions].
- [10] Sciensano. (2025, September 9). Causes of death (For a Healthy Belgium).
- [11] Statistisches Bundesamt. (2025, October 15). Todesursachen 2024: Immer mehr Menschen versterben an Demenz [Causes of death 2024: More and more people are dying of dementia].
- [12] Gemeinsamer Bundesausschuss. (2025, February 12). Arzneimittel-Richtlinie, Anlage III: Übersicht über Verordnungseinschränkungen und -ausschlüsse [Pharmaceuticals Directive, Annex III: Overview of prescription restrictions and exclusions].
- [13] Ministry of Health, Labour and Welfare. (2025, September 16). 令和6年(2024)人口動態統計(確定数)の概況 [Overview of 2024 vital statistics (final data)].
- [14] ISTAT. (2026, September 30). Cause di morte in Italia: Anno 2023 [Causes of death in Italy: Year 2023].
- [15] Gazzetta Ufficiale della Repubblica Italiana. (2025, March 21). Agenzia Italiana del Farmaco, Determina 4 marzo 2025 (n. 252/2025): Modifica dei prescrittori per i medicinali a base dei principi attivi evolocumab, alirocumab e inclisiran, autorizzati con regime di fornitura RRL
- [16] Eli Lilly and Company. (2026, May 25). A single dose of Lilly’s PCSK9 base editor, VERVE-102, reduced PCSK9 by up to 88% and LDL-C by up to 62%, with durable effects supporting its potential as a one-time treatment for hypercholesterolemia.
This Report Answers
- The report explains how cholesterol lowering biologic drugs are used by drug type, application and distribution channel.
- Segment analysis identifies the subsegment that leads each segment and the clinical reasons behind its 2026 share.
- Country analysis compares the seven listed countries through reimbursement, prescriber rules and cardiovascular disease burden.
- Competitive analysis reviews antibody, siRNA and oral drug developers along with gene editing programs.
- Treatment analysis assesses how outcome evidence, dosing frequency and cost shape prescribing.
What does the Cholesterol Lowering Biologic Drugs Market cover?
The Cholesterol Lowering Biologic Drugs Market covers prescription therapies that reduce LDL cholesterol in patients with hypercholesterolemia or cardiovascular disease. It forms part of the wider dyslipidemia therapeutics field and focuses on PCSK9, ANGPTL3 and CETP mechanisms.
Oral PCSK9 peptides such as enlicitide are counted under PCSK9 Inhibitors, and oral CETP small molecules are counted under CETP Inhibitors.
What is included in the scope?
The scope includes prescription therapies sold for LDL cholesterol or cardiovascular risk reduction in adults and in pediatric familial hypercholesterolemia where labeled. Values are measured at manufacturer revenue level.
Drug sold in prefilled syringes and pens is valued as finished product. Overlap with the broader lipid metabolism modulators category is limited to these mechanisms.
What is excluded from the scope?
The scope excludes conventional lipid-lowering drugs such as statins, ezetimibe, bempedoic acid and fibrates. Nutraceuticals, dietary supplements and over-the-counter products are also excluded.
Lipoprotein apheresis equipment falls outside the revenue boundary. Diagnostic tools such as point of care lipid tests are excluded, along with devices such as coronary stents used after a cardiac event.
How Was the Analysis Built?
The analysis draws on 120+ sources, 35+ company portfolios, 25+ countries, and more than 20 industry interviews.
- Primary Research: Primary research includes discussions with manufacturers, service providers, technology developers, distributors, end users, and subject-matter experts. These conversations examine purchasing priorities, product adoption, operational challenges, approval requirements, competitive positioning, and the factors that influence wider market acceptance.
- Desk Research: Desk research covers government statistics, regulatory publications, company filings, trade data, technical studies, industry associations, standards, public policy, and other authoritative sources. Every source used in the analysis is documented in the bibliography.
- Market Sizing and Forecasting: Market estimates combine historical performance, demand indicators, pricing and volume trends, segment shares, company participation, country-level growth, adoption patterns, investment activity, and barriers to market expansion.
- Data Validation and Update Cycle: Findings are validated by comparing primary interviews with public data, company activity, regulatory changes, trade patterns, and industry developments. Regular updates review new product launches, capacity changes, partnerships, approvals, and shifts in commercial adoption.
What is the report’s scope and coverage?
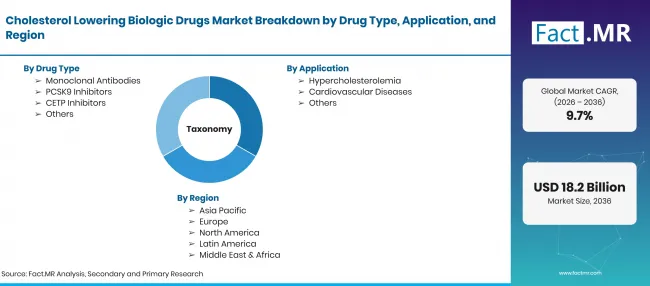
Cholesterol Lowering Biologic Drugs Market Taxonomy (1) | Source: Fact.MR
| Attribute | Details |
|---|---|
| Quantitative Units | USD billion in 2026 to USD billion by 2036 at a CAGR |
| Market Definition | Prescription therapies that lower LDL cholesterol by acting on PCSK9, ANGPTL3 or CETP, sold as injectable antibodies, siRNA, oral PCSK9 peptides and oral CETP inhibitors. The scope covers use in hypercholesterolemia and cardiovascular disease through retail, hospital and online pharmacies. |
| Drug Type | Monoclonal Antibodies; PCSK9 Inhibitors; CETP Inhibitors |
| Application | Hypercholesterolemia; Cardiovascular Diseases |
| Distribution Channel | Retail Pharmacies; Hospital Pharmacies; Online Pharmacies |
| Regions Covered | North America; Latin America; Western Europe; Eastern Europe; East Asia; South Asia & Pacific; Middle East & Africa |
| Countries Covered | United States; United Kingdom; Sweden; Belgium; Germany; Japan; Italy |
| Key Companies Profiled | Amgen Inc.; Regeneron Pharmaceuticals Inc.; Sanofi S.A.; Novartis AG; Merck & Co., Inc.; AstraZeneca plc; Eli Lilly and Company (including Verve Therapeutics); NewAmsterdam Pharma Company N.V. |
| Forecast Period | 2026 to 2036 |
| Approach | Hybrid top-down and bottom-up approach using treated patient volumes; drug type revenue; application and channel mix; country reimbursement conditions; and manufacturer portfolio review. |
How is the market segmented?
-
By Drug Type
- Monoclonal Antibodies
- PCSK9 Inhibitors
- CETP Inhibitors
-
By Application
- Hypercholesterolemia
- Cardiovascular Diseases
-
By Distribution Channel
- Retail Pharmacies
- Hospital Pharmacies
- Online Pharmacies
-
By Region
- North America
- Latin America
- Western Europe
- Eastern Europe
- East Asia
- South Asia & Pacific
- Middle East & Africa

